On weight, retatrutide wins in trials, but no head-to-head study exists. In people with type 2 diabetes, The Lancet's TRIUMPH-2 paper reports −18.8% at 80 weeks on 12 mg retatrutide. Tirzepatide's SURMOUNT-2 reported −14.7% at 72 weeks on 15 mg, measured the same way. Without diabetes the figures are −25.0% (TRIUMPH-1) and −20.9% (SURMOUNT-1). Retatrutide costs more in tolerability and is not approved anywhere; Lilly plans to file in Q1 2027. Tirzepatide is FDA-approved as Zepbound and Mounjaro.
Retatrutide vs tirzepatide: which is better?
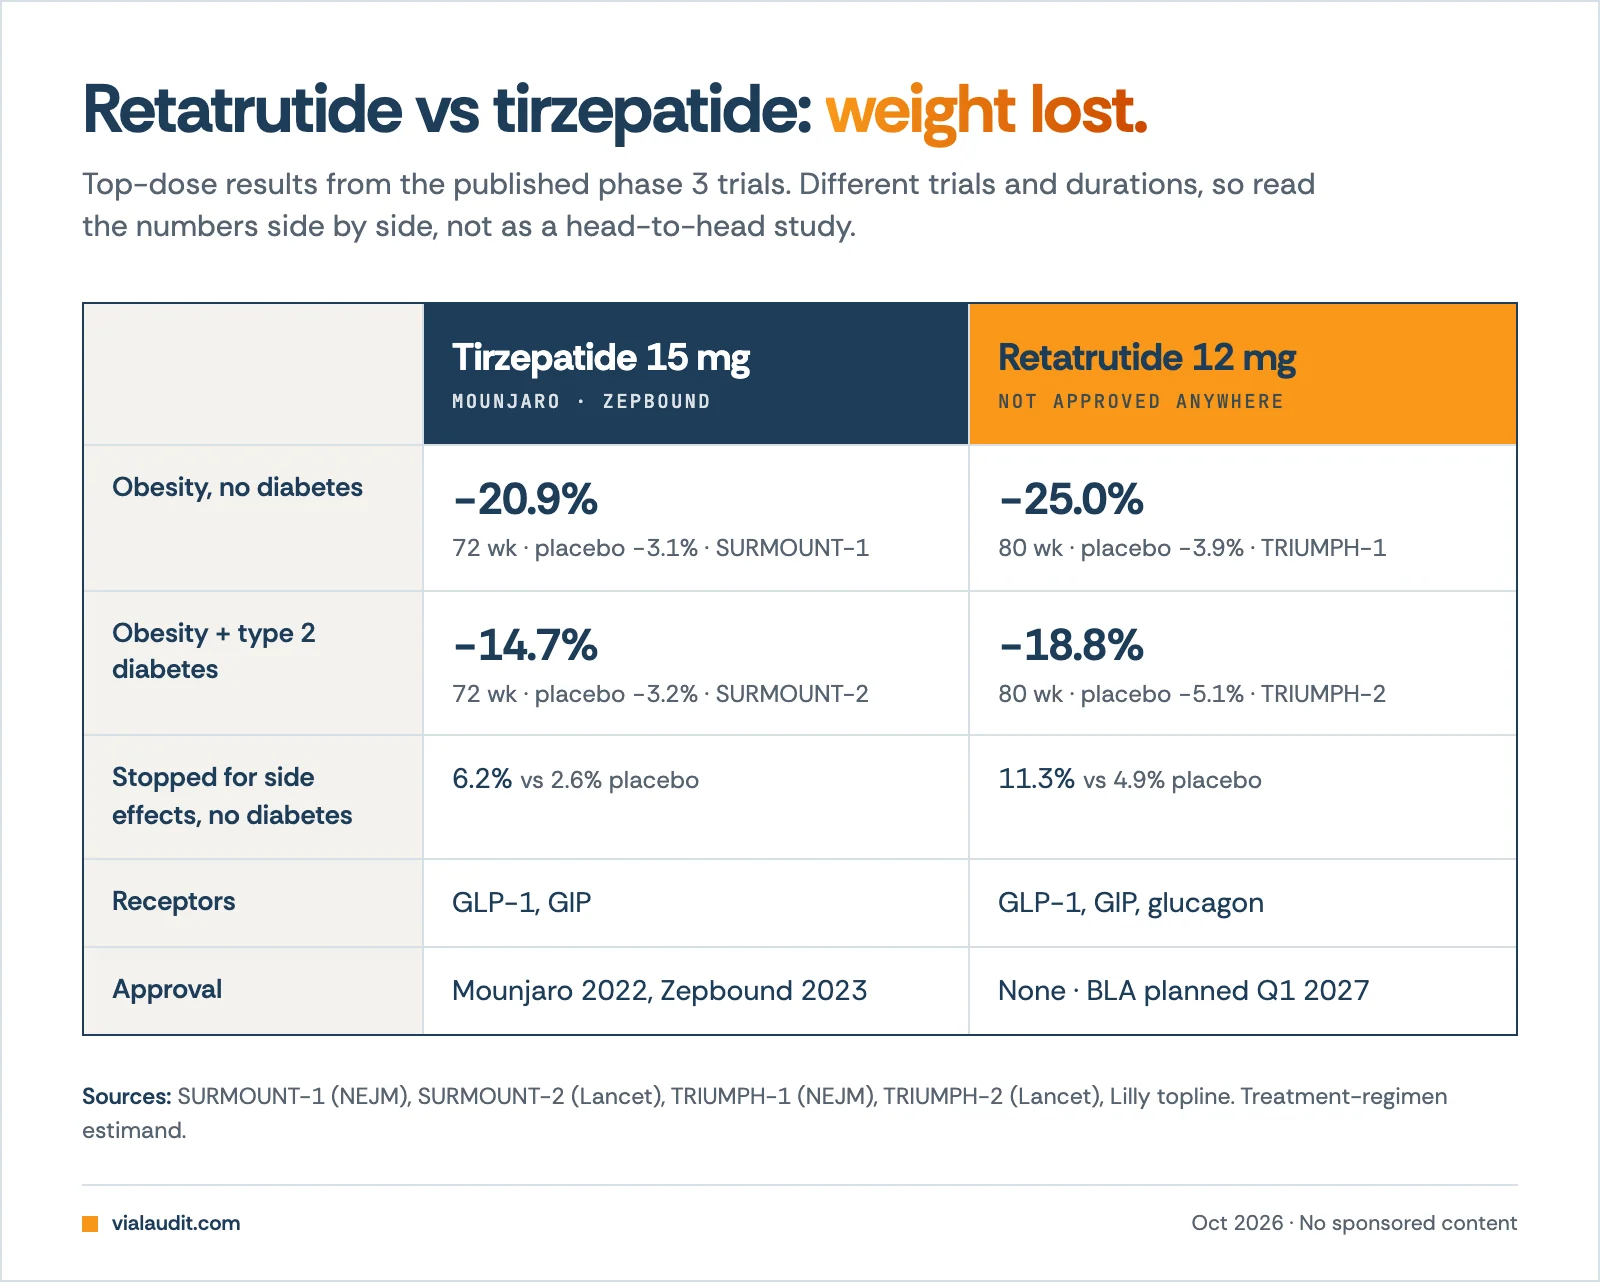
| Week 72–80, top dose, treatment-regimen estimand | Tirzepatide 15 mg | Retatrutide 12 mg |
|---|---|---|
| Obesity, no diabetes | −20.9% at 72 wk vs −3.1% placebo (SURMOUNT-1) | −25.0% at 80 wk vs −3.9% placebo (TRIUMPH-1) |
| Obesity + type 2 diabetes | −14.7% at 72 wk vs −3.2% placebo (SURMOUNT-2) | −18.8% at 80 wk vs −5.1% placebo (TRIUMPH-2) |
| Stopped for side effects, top dose, no diabetes | 6.2% vs 2.6% placebo | 11.3% vs 4.9% placebo (Lilly topline) |
| Stopped for side effects, top dose, type 2 diabetes | under 5% across arms | 8% vs 5% placebo (includes deaths) |
| Receptors | GLP-1, GIP | GLP-1, GIP, glucagon |
| Approval | Mounjaro 2022, Zepbound 2023 | none; BLA planned Q1 2027 |
Every number in the weight rows uses the treatment-regimen estimand. The Lancet paper reports −18.8% on 12 mg at week 80 under the treatment-regimen estimand, which counts every randomised participant whether or not they stayed on the drug. Lilly's headline 20.8% uses the efficacy estimand, which estimates the effect had everyone stayed on treatment. For TRIUMPH-1 the same split is 25.0% (NEJM) against Lilly's 28.3%. Mixing the two bases is the most common error in retatrutide comparisons, and earlier versions of this page made it.
No head-to-head trial exists. The retatrutide trials ran eight weeks longer than the tirzepatide trials and enrolled different people in different years. Read the gap as an order of magnitude, not a ranking.
How do the mechanisms differ?
Both come from Eli Lilly. Tirzepatide activates two receptors, GLP-1 and GIP. Retatrutide activates those two plus the glucagon receptor. Glucagon-receptor activity is proposed to raise energy expenditure on top of the appetite effects of the other two, and it is the usual explanation for the larger weight loss.
The third receptor also shows up in the side-effect profile. The TRIUMPH papers flag dysesthesia (an abnormal skin sensation, up to 7% on 12 mg in TRIUMPH-2) and hypotension (up to 6%) alongside the GI events both drugs share. The NEJM TRIUMPH-1 paper reports that mean pulse rate rose and peaked around week 20 before falling. Details are on our retatrutide side effects page.
How do you switch from tirzepatide to retatrutide?
No published trial describes it. The Phase 3 record has one starting point: TRIUMPH-2 began every participant on 2 mg retatrutide weekly and stepped up every four weeks, through 4, 6 and 9 mg to 12 mg at week 16 (Lilly, 29 September 2026). The full ladder is in retatrutide dosing protocols.
On Reddit, the question is usually about dose equivalence. An r/Peptides thread titled "Switching from tirz to Reta" (1vegnt1) asks whether someone on 5 mg tirzepatide should start reta at 1 mg. No conversion between the two drugs has been published, and the milligrams are not interchangeable: the molecules differ in potency at each receptor.
Switching also changes the supply chain. Tirzepatide can come from a pharmacy. Retatrutide, outside a trial or Lilly's expanded-access program, comes from a research-peptide vendor with no regulatory oversight. Our mirror of 58 public Janoshik retatrutide tests found measured content between 87.8% and 143.5% of the label. The vial is a bigger variable than the switching schedule.
Should I add reta to a stalled tirz 15 mg?
The trials do not test it. An r/Peptides thread, "3+ month weight loss stall on tirz 15mg. Add reta?" (1vcto5c), asks the question directly.
What the pharmacology says: retatrutide already contains tirzepatide's two receptor actions. Adding it to tirzepatide puts two agonists on the GLP-1 and GIP receptors at once, plus glucagon-receptor activity. GI side effects in both drug programs rise with dose, and stacking raises the combined dose without any trial measuring the result. Reddit threads such as "Reta + Tirz … what is the doses you use" (1w9impa) show people doing it. None of them can report what was in the vials.
What about eloraTZP?
Lilly is also developing eloralintide, an amylin-receptor agonist, and testing it alongside tirzepatide. A September r/Retatrutide thread titled "Retatrutide is being dethroned by eloraTZP (tirzepatide + eloralintide)" (1wu8znx) drew hundreds of comments. We check those claims against the published data in eloralintide vs retatrutide.
Regulatory state, October 2026
Tirzepatide. FDA-approved as Mounjaro for type 2 diabetes (2022) and as Zepbound for chronic weight management (2023), available on prescription. FDA declared the tirzepatide shortage resolved in December 2024, which ended the legal basis for most mass compounding. Our 503A and PCAC analysis tracks where compounded tirzepatide stands now.
Retatrutide. Not approved anywhere. Lilly's 29 September 2026 release says it "plans to submit a Biologics License Application (BLA) in Q1 2027." Under standard review, a decision would follow in late 2027 or 2028. Retatrutide is not eligible for 503A compounding. Lilly sued six online sellers in August 2026, and FDA's 24 August 2026 warning letters named retatrutide under code names such as "GLP-3 RT", covered in GLP-3 RT is retatrutide.
What is known and what is pending?
Known for tirzepatide. Multi-year Phase 3 data in obesity and diabetes, post-approval experience since 2022, and an established dose ladder (2.5 mg start, +2.5 mg every four weeks to 15 mg).
Known for retatrutide. Phase 2 (NEJM 2023), four Phase 3 readouts, and two full Phase 3 papers (TRIUMPH-1 in NEJM and TRIUMPH-2 in The Lancet, both 29 September 2026). The full readout is in retatrutide Phase 3 results.
Pending for retatrutide. A cardiovascular outcomes result; data beyond the 104-week TRIUMPH-1 extension; the TRIUMPH-2 sleep apnea results; and any head-to-head trial against tirzepatide.
What we read
The SURMOUNT-1 (NEJM 2022) and SURMOUNT-2 (The Lancet 2023) abstracts; the TRIUMPH-1 (NEJM) and TRIUMPH-2 (The Lancet) papers of 29 September 2026; Lilly's TRIUMPH releases from December 2025 to September 2026; the Phase 2 retatrutide paper (NEJM 2023); and the Reddit threads linked above, read between August and October 2026. We did not read either drug's full supplementary appendix.
Sources
- Jastreboff et al., TRIUMPH-1, NEJM, 29 September 2026 (doi 10.1056/NEJMoa2604169)
- Bellido et al., TRIUMPH-2, The Lancet, 29 September 2026 (doi 10.1016/S0140-6736(26)01861-1)
- Eli Lilly, TRIUMPH-2 release, 29 September 2026
- Jastreboff et al., SURMOUNT-1, NEJM 2022
- Garvey et al., SURMOUNT-2, The Lancet 2023
- Jastreboff et al., retatrutide Phase 2, NEJM 2023
- FDA approval documents, Mounjaro and Zepbound
- Reddit: switching 1vegnt1, stall on tirz 15 mg 1vcto5c, reta + tirz 1w9impa, switching back for fatigue 1wci1lz, eloraTZP 1wu8znx
- Internal: retatrutide Phase 3 results, retatrutide dosing protocols, retatrutide side effects, eloralintide vs retatrutide, tirzepatide vs semaglutide, 503A and PCAC
Frequently asked
Is retatrutide better than tirzepatide for weight loss?
In separate trials, yes. Measured the same way (treatment-regimen estimand), retatrutide 12 mg produced −25.0% at 80 weeks in TRIUMPH-1 against −20.9% at 72 weeks for tirzepatide 15 mg in SURMOUNT-1. No trial has compared them directly, populations and durations differ, and retatrutide had a higher dropout rate for side effects.
How do you switch from tirzepatide to retatrutide?
No published trial describes a switch. In TRIUMPH-2 every participant started retatrutide at 2 mg weekly and stepped up every four weeks. A Reddit thread titled "Switching from tirz to Reta" asks whether a person on 5 mg tirzepatide should start at 1 mg. The trial record does not answer that question.
Can you take retatrutide and tirzepatide together?
No trial has tested the combination. Retatrutide already activates the GLP-1 and GIP receptors that tirzepatide targets, so stacking them adds a second agonist on the same two receptors. Reddit threads such as "Reta + Tirz … what is the doses you use" describe people doing it on unverified product, with no safety data behind them.
Should I add retatrutide to a stalled tirzepatide 15 mg dose?
The trials do not test add-on use. Retatrutide adds glucagon-receptor action, which is the proposed source of its larger effect, but it also repeats tirzepatide's two receptors. A Reddit thread asks exactly this ("3+ month weight loss stall on tirz 15mg. Add reta?"). Stalls on an approved drug belong with the prescriber.
Why do some people switch back from retatrutide to tirzepatide?
Tolerability is the reason users give. A Reddit thread titled "Thinking of Switching from R to Tirz" cites fatigue. In the trials, more people stopped retatrutide for side effects: 11.3% on 12 mg in TRIUMPH-1 (Lilly topline) against 6.2% on tirzepatide 15 mg in SURMOUNT-1.
Is retatrutide FDA approved?
No. Lilly's 29 September 2026 release says it "plans to submit a Biologics License Application (BLA) in Q1 2027." Standard review would place a decision in late 2027 or 2028. Tirzepatide has been FDA-approved since 2022 (Mounjaro, type 2 diabetes) and 2023 (Zepbound, weight management).