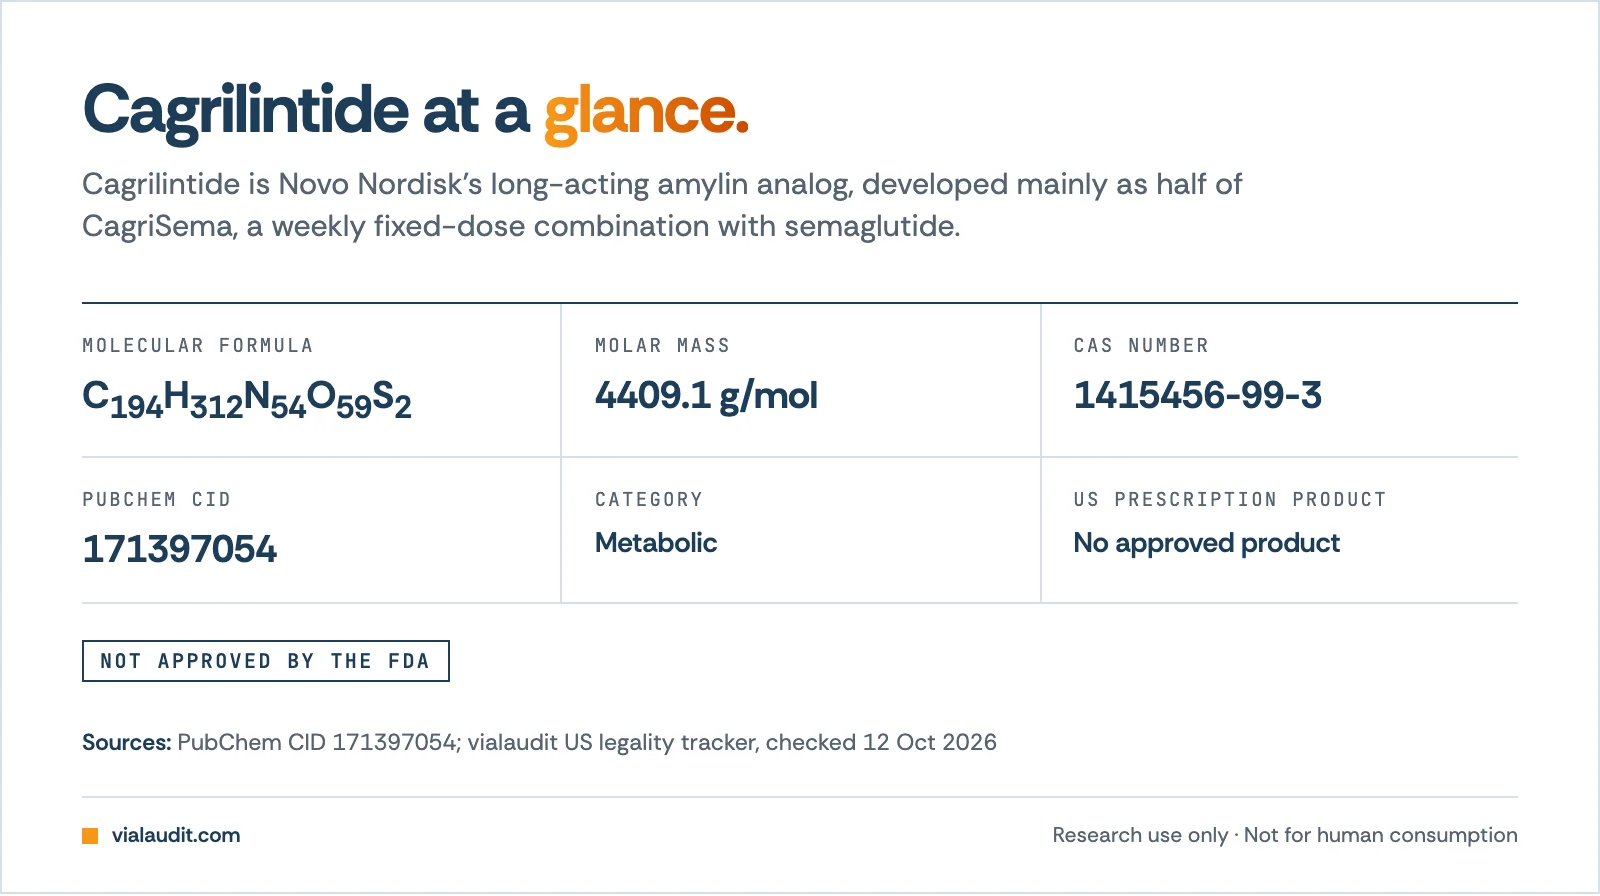
Cagrilintide is Novo Nordisk's long-acting amylin analog, developed mainly as half of CagriSema, a weekly fixed-dose combination with semaglutide. Novo filed CagriSema 2.4/2.4 mg for weight management with the FDA in December 2025 and guides to a US decision in Q4 2026; no decision had been announced as of 5 October 2026. On 21 September 2026 Novo reported CagriSema 1.0/1.0 mg beat tirzepatide 5 mg on weight loss (12.4% vs 9.1%), but the 2.4/2.4 mg dose missed non-inferiority against tirzepatide 15 mg in February. FDA says cagrilintide cannot be compounded.
Research notes
What is the status of CagriSema in October 2026?
CagriSema is under FDA review, and Novo Nordisk expects a decision in Q4 2026. No decision had been announced as of 5 October 2026.
| Milestone | Date | Source |
|---|---|---|
| NDA filed for weight management (2.4/2.4 mg) | December 2025 | Novo, 21 Sep 2026 |
| REDEFINE 4 vs tirzepatide 15 mg: non-inferiority not met | 23 Feb 2026 | Novo announcement 13/2026 |
| REIMAGINE 5 and REDEFINE 9 topline | 21 Sep 2026 | Novo, 21 Sep 2026 |
| US FDA decision | expected Q4 2026 | Novo Capital Markets Day deck |
| REDEFINE 11 readout | expected Q1 2027 | same deck |
| High-dose CagriSema readout | expected H1 2028 | same deck |
We will update this block when FDA acts.
When will CagriSema be approved?
If FDA approves on Novo's timeline, before the end of 2026. Novo filed the New Drug Application in December 2025 and has said since then that it expects a decision in Q4 2026, most recently in its 21 and 30 September releases. FDA does not announce review dates in advance, so the exact day is unknown. Third-party trackers that print a specific October or December date are estimating, not quoting FDA or Novo.
An approval would cover CagriSema, the fixed combination, at the filed 2.4/2.4 mg dose for weight management. It would not approve cagrilintide on its own, and it would not change the status of research-grade cagrilintide vials.
What did the September 2026 trials show?
Novo released two Phase 3 readouts on 21 September 2026, both at the low 1.0/1.0 mg dose. Novo reports both figures on the efficacy estimand, which assumes participants stayed on treatment.
| Trial | Population | Comparison | Weight loss | Week |
|---|---|---|---|---|
| REIMAGINE 5 | Type 2 diabetes on metformin and/or SGLT2i | CagriSema 1.0/1.0 mg vs tirzepatide 5 mg | 12.4% vs 9.1% (superior) | 60 |
| REDEFINE 9 | Overweight or obesity | CagriSema 1.0/1.0 mg vs placebo | 21.0% vs 2.0% | 68 |
REIMAGINE 5 also showed HbA1c falling 1.71 points on CagriSema against 1.67 on tirzepatide, which Novo reports as non-inferior.
The tirzepatide comparison needs its context. Tirzepatide 5 mg is that drug's lowest maintenance dose. At full dose the picture reverses: in REDEFINE 4 (open-label, 809 people, 84 weeks), CagriSema 2.4/2.4 mg produced 20.2% weight loss against 23.6% for tirzepatide 15 mg on the treatment-regimen estimand (23.0% vs 25.5% if all participants adhered). The trial missed its primary endpoint of non-inferiority. CagriSema beat a low dose of tirzepatide; it has not matched the top one.
How does cagrilintide work?
Cagrilintide is a synthetic long-acting amylin analog developed by Novo Nordisk. Amylin is a hormone co-secreted with insulin from pancreatic beta cells; it slows gastric emptying and promotes satiety through a different receptor system than GLP-1 (the amylin and calcitonin receptors).
CagriSema pairs amylin-receptor activation (cagrilintide) with GLP-1 receptor activation (semaglutide), targeting two satiety pathways at once. Cagrilintide alone is studied far less than the combination, and most research-vendor listings position it as a compound to stack with semaglutide.
What doses are used in research?
The Phase 2 dose-escalation literature spans 0.16 mg to 4.5 mg weekly subcutaneous. The Phase 3 CagriSema program uses fixed combinations: 1.0/1.0 mg (REIMAGINE 5, REDEFINE 9), 1.7/1.7 mg (an arm of REDEFINE 9) and 2.4/2.4 mg (REDEFINE 4 and the filed dose). Novo is now testing a higher-dose combination, with results expected in the first half of 2028.
Trials escalate the dose stepwise; direct starts at higher doses produce more gastrointestinal side effects. A half-life of about seven days supports weekly administration, the same schedule as semaglutide.
What are the known side-effect concerns?
Reported side effects from Phase 2 and Phase 3 trials follow the GLP-1-class pattern:
- Nausea, vomiting, diarrhea: the most common, dose-dependent and concentrated in titration
- Injection-site reactions at higher doses
- No distinct cardiovascular signal in published data, in contrast to the heart-rate rise reported for retatrutide
Novo described CagriSema as "well tolerated overall" in both September trials, with a safety profile consistent with earlier studies. Novo has not released full adverse-event tables for those two trials.
Can cagrilintide be compounded?
No. FDA's GLP-1 page says "retatrutide and cagrilintide cannot be used in compounding under federal law." FDA's June 2025 letter to state medical boards explains why: cagrilintide has no USP monograph, is not a component of an approved drug, and is on neither the 503A nor the 503B bulks list.
FDA has not said how a CagriSema approval would affect that position. For how FDA treated compounded copies of semaglutide and tirzepatide once those drugs were approved and available, see our 503A and PCAC analysis.
Do people stack cagrilintide with retatrutide?
Some do. A September 2026 r/Retatrutide thread discussed running cagrilintide alongside retatrutide.
No trial has tested that combination. CagriSema's doses were chosen for pairing with semaglutide, a single GLP-1 agonist. Retatrutide already hits GLP-1, GIP and glucagon receptors, and its own trial doses were set without an amylin partner. Neither program's safety data describe the stack.
The amylin class is also moving past cagrilintide. Lilly's eloralintide, tested with tirzepatide, is the comparison most Reddit threads now make; see eloralintide and eloraTZP vs retatrutide. For the incretin-only comparison, see retatrutide vs tirzepatide.
How pure is the cagrilintide being sold?
Public Janoshik testing data on cagrilintide is sparse: one publicly submitted test in our mirror as of May 2026. Until more vendors submit batches, vendor audits for cagrilintide rely on identity confirmation alone, and cross-vendor purity comparison is not meaningful at that sample size. All vials referenced are research-grade reagents and are not intended for human consumption.
What it's researched for
- weight management research
- amylin-analog studies
- GLP-1 combination protocols
Where to source it
ALL 6 VENDORS →RANKED BY COMPOSITE SCORE · PRICES ARE SNAPSHOTS FROM THE PRICE INDEX · PER-MG IS A WITHIN-COMPOUND COMPARATOR
Frequently asked about Cagrilintide
When will CagriSema be approved?
Novo Nordisk filed a New Drug Application with the FDA in December 2025 and says a decision is expected in Q4 2026. It repeated that guidance on 21 and 30 September 2026. As of 5 October 2026 no FDA decision had been announced. Approval would cover CagriSema, not cagrilintide sold on its own.
Is CagriSema better than tirzepatide?
It depends on the dose. In REIMAGINE 5, CagriSema 1.0/1.0 mg produced 12.4% weight loss against 9.1% for tirzepatide 5 mg at week 60 in type 2 diabetes. In REDEFINE 4, CagriSema 2.4/2.4 mg failed to show non-inferiority against tirzepatide 15 mg at 84 weeks: 20.2% against 23.6% on the treatment-regimen estimand.
What is cagrilintide?
Cagrilintide is a synthetic long-acting amylin analog developed by Novo Nordisk. Amylin is a hormone co-secreted with insulin from pancreatic beta cells. Cagrilintide mimics its activity at amylin and calcitonin receptors, with a half-life of about seven days that supports once-weekly dosing in trials.
Can cagrilintide be compounded?
No. FDA states that "retatrutide and cagrilintide cannot be used in compounding under federal law." Cagrilintide has no USP monograph, is not part of an approved drug and is not on either bulks list. A clinic or telehealth service offering compounded cagrilintide is selling something FDA says does not qualify for the compounding exemptions.
Is cagrilintide FDA-approved?
No. Cagrilintide is not approved by the FDA, EMA or any regulator, alone or in combination. CagriSema is under FDA review with a decision guided for Q4 2026. Cagrilintide sold online today is research-grade material with no approved label and no regulator-checked supply chain.
Do people stack cagrilintide with retatrutide?
Some do, judging by r/Retatrutide threads in September 2026. No trial has tested the combination. CagriSema pairs cagrilintide with semaglutide, a single GLP-1 agonist, and its doses were set for that pairing. Retatrutide already acts on GLP-1, GIP and glucagon receptors, so trial data for either drug do not describe the stack.